
Smoking MARPE outcomes
need disciplined
risk assessment
A practical framework for nicotine exposure, palatal anchorage, CBCT interpretation, and documented treatment uncertainty.
TL;DR Smoking MARPE outcomes cannot be quantified from the available expansion studies, but nicotine exposure warrants explicit risk assessment before skeletal anchorage. Delayed tissue healing and poorer osseointegration may compromise TAD stability. Use CBCT-based site planning, assess hygiene and systemic risks, document uncertainty, and maintain a contingency pathway if separation or anchorage fails.
An adult seeking palatal expansion may present with a smoking history, nicotine use, marginal hygiene, and a request to avoid a surgical route. That combination turns routine appliance selection into a risk-management decision. This guide from Dr. Mark Radzhabov at ortodontmark.com addresses smoking MARPE outcomes through the evidence that is actually available: TAD healing concerns, CBCT planning, suture assessment, and transparent consent. It helps the orthodontist separate documented findings from assumptions when choosing skeletal expansion for a nicotine-exposed adult.
What is the real evidence
boundary
for smoking and MARPE?
Smoking MARPE outcomes are the clinical healing, anchorage, and skeletal-response considerations that must be assessed when nicotine exposure accompanies miniscrew-assisted palatal expansion. The supplied expansion literature reports separation, skeletal and dentoalveolar changes, but it does not report a smoking-specific separation rate, TAD survival rate, or nicotine dose threshold. A clinician should therefore avoid presenting smoking as a measured predictor from these studies.
Dr. Radzhabov’s course identifies smoking among adult risk factors because smokers may have delayed tissue healing and poor osseointegration. This is clinically relevant where appliance stability depends on palatal TAD fixation. It is not evidence that nicotine exposure automatically contraindicates treatment.
Chun et al. (2022) found midpalatal separation in 95% of the MARPE arm after the stated expansion protocol, but that result cannot be reassigned to nicotine-exposed adults. The useful conclusion is narrower: establish baseline risk, explain uncertainty, and retain a change-of-plan pathway.
Which nicotine-exposed case still
justifies
a MARPE pathway?
Smoking history should be reviewed alongside systemic health, oral hygiene, palatal anatomy, and the anticipated need for stable skeletal anchorage. Diabetes mellitus and selected psychiatric or systemic diseases are also course-listed adult risk factors. Poor hygiene raises concern for mucosal and gingival inflammation, which may contribute to TAD loss.
CBCT should guide the decision. Evaluate the median palatal suture in axial, coronal, and sagittal views. Inspect bone volume at proposed insertion sites. And identify the incisive canal. The suture stage is not interchangeable with chronological age. Govaerts et al. (2023) found closed sutures in 61% of female subjects aged 15 years, illustrating why an age-only rule is unsafe.
Jeon et al. (2022) reported that older age was associated with nonseparation in males but not females. In a nicotine-exposed adult, this supports layered risk assessment rather than a single exclusion criterion.
How should nicotine miniscrew stability
shape
palatal TAD planning?
Dr. Radzhabov’s protocol begins with a site that offers suitable bone rather than adapting the site to a preferred appliance. The anterior hard palate is the safest and most studied region, while the posterior palate has greater vascular density and is less attractive for placement. Avoid tooth-root contact and examine CBCT before insertion.
The T-zone is the preferred palatal field because it combines favorable bone and soft-tissue conditions while avoiding root interference. The course advises an insertion inclination of about 15 degrees so that the screw traverses the maximum amount of bone. Bicortical fixation is a stated objective when anatomy permits.
Place the proposed screws virtually when several TADs are required. A surgical guide based on CBCT allows planned positioning and can support single-stage placement of the skeletal expansion appliance. Nicotine exposure makes this precision more valuable because it reduces avoidable instability variables.
When should smoking orthodontic bone healing
change
consent and follow-up?
The consent discussion should distinguish a plausible healing risk from a documented smoking-specific MARPE outcome. Explain that delayed tissue healing and poor osseointegration are reasons for heightened caution, while the supplied evidence does not establish a nicotine-specific probability of separation, relapse, or failure.
Chun et al. (2022) obtained CBCT before treatment, immediately after expansion, and after a 3-month consolidation period. Their MARPE group showed less buccal displacement of anchor teeth and a lower decrease in skeletal, dentoalveolar, and periodontal variables after consolidation. These findings support structured imaging and stability review, not a smoking-specific prognosis.
If anchorage becomes mobile, inflammation develops, or separation is not achieved, reassess rather than continue an assumed successful protocol. Benetti et al. (2024) notes increased complication risk and high biological costs with SARPE, so surgical referral is a deliberate contingency decision rather than a casual default.
Why does adult palatal expansion risk
remain
individual with nicotine exposure?
The main decision is not whether every nicotine-exposed adult can receive MARPE. It is whether the patient’s suture morphology, bone volume, mucosal condition, hygiene, systemic risk profile, and treatment alternatives support a carefully documented attempt at skeletal anchorage.
Jeon et al. (2022) reported separation in 61.05% of males and 94.17% of females. The sex-associated difference and age relationship reinforce the need to avoid uniform predictions. Nicotine exposure adds a healing concern to an already variable biological response.
For airway claims, remain equally restrained. Benetti et al. (2024) reported nasal-cavity volume increases ranging from 31% to 9.9% across included studies, while only one study assessed maintenance after one year. Airway change should not be used to offset an inadequately assessed anchorage risk.
Free Clinical Guide
Which Expansion Appliance at Which Age?
Get Dr. Mark Radzhabov's guide to skeletal-expansion appliances — indications, pros & cons, and how to choose by patient age. Free to your inbox.
Prefer video? Watch the free demo lesson on MARPE appliance types, features and trade-offs.
Documented outcomes
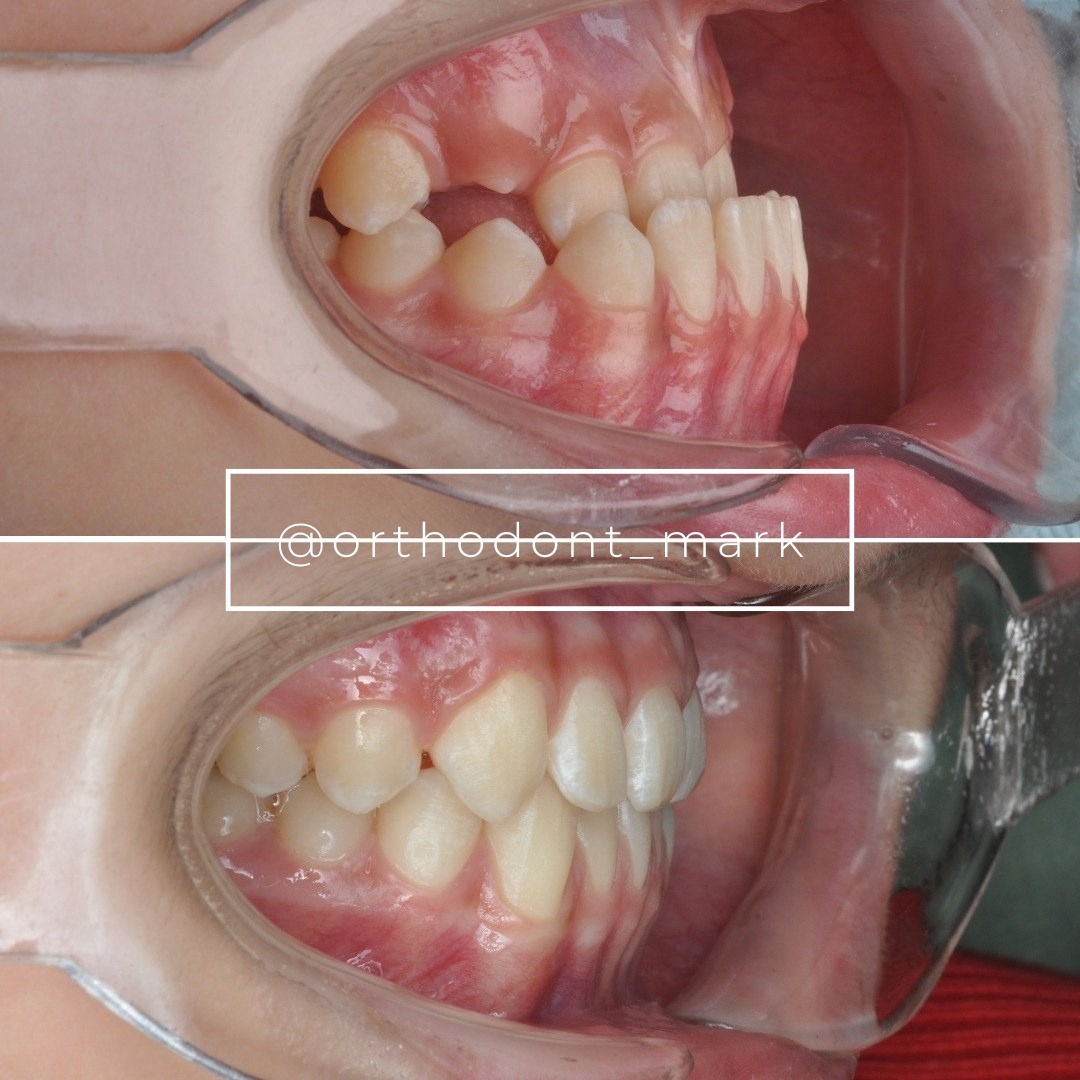
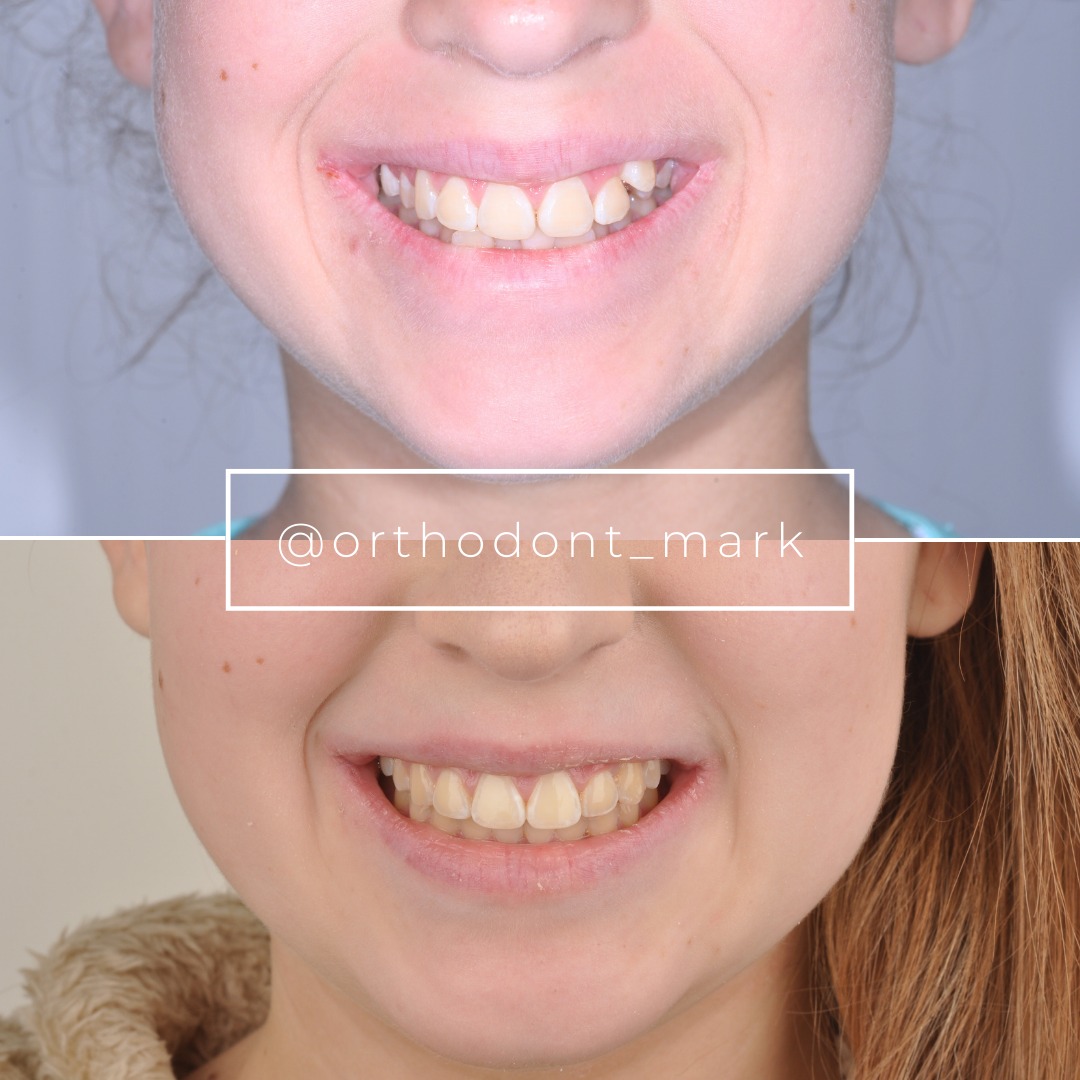
Clinical cases from Dr. Mark Radzhabov's practice

Learn the full MARPE protocol from Dr. Mark Radzhabov
Fundamental course covering CBCT patient selection, miniscrew planning, activation protocols, and 60+ clinical cases. Choose the access level that fits your practice.
Essentials of rapid palatal expansion for practicing orthodontists.
- Core RPE concepts and biomechanics
- 6 structured video lessons
- Clinical decision checklists
- Lifetime access to recordings
Deep-dive into MARPE protocol, diagnostics, and clinical execution.
- 6 modules covering MARPE from A to Z
- CBCT case selection walkthroughs
- Miniscrew placement and activation
- 60+ annotated clinical cases
- Direct Q&A with Dr. Mark Radzhabov
5-element medical consultation framework for dentists and orthodontists.
- Trust-building consultation protocol
- 5 lesson modules
- Templates for treatment plan delivery
- Works with any clinical specialty
Clinical FAQ
Does smoking affect MARPE success rates in adults?
The supplied evidence does not report a smoking-specific MARPE success rate. Dr. Radzhabov’s protocol treats smoking as an adult risk factor because delayed healing and poor osseointegration may compromise TAD stability.
How does nicotine impact miniscrew stability during palatal expansion?
Nicotine exposure warrants caution because the course identifies delayed tissue healing and poor osseointegration in smokers. CBCT-guided site selection, hygiene assessment, and monitoring for inflammation or mobility are clinically important.
Should smokers be excluded from MARPE treatment?
Smoking alone should not be presented as an automatic exclusion from MARPE. The decision should incorporate suture assessment, palatal bone, mucosal condition, hygiene, systemic health, anchorage design, and an explicit contingency plan.
How should smoking and midpalatal suture healing after skeletal expansion be discussed in consent?
Explain that smoking is a healing and osseointegration concern, while direct smoking-specific evidence for midpalatal separation or post-expansion healing is not supplied. Avoid numerical promises and document the possibility of altered treatment planning.
What are informed consent considerations for smokers undergoing MARPE?
Consent should cover uncertainty about nicotine-related skeletal response, potential healing and anchorage concerns, hygiene expectations, imaging review, monitoring, and the possibility that an alternative pathway may be required.
Which CBCT findings matter for adult palatal expansion risk factors?
Assess median palatal suture morphology, palatal width and thickness, bone volume at planned insertion sites, the incisive canal, and the relationship of proposed screws to roots and soft tissues.
How should MSE expansion smoking patients be planned digitally?
Virtually position palatal TADs on CBCT and use a surgical guide when appropriate. This supports precise placement, especially when multiple screws are used, and reduces avoidable instability variables.
Is smoking an adult palatal expansion contraindication?
The course lists smoking as an adult risk factor rather than an absolute contraindication. The clinician should assess healing risk, osseointegration, hygiene, anatomy, and whether skeletal anchorage can be planned safely.
What does tobacco use skeletal anchorage change in appliance selection?
Tobacco use should increase attention to stable palatal anchorage, bone volume, mucosal thickness, and appliance fit. It should also lower tolerance for poorly planned placement or unsupported claims of predictable success.
How should MARPE failure risk smoking patients be managed?
Monitor tissue condition and TAD stability, reassess CBCT and appliance mechanics if concerns emerge, and avoid continuing on the assumption that separation will occur. Discuss alternative treatment pathways before activation.
Nicotine exposure should change the quality of the MARPE conversation, even where direct evidence does not quantify its effect on separation or appliance survival. Dr. Mark Radzhabov’s approach is to identify healing and osseointegration risk, plan anchorage from CBCT, and avoid promising a predictable split solely from age or appliance choice. Bring a nicotine-exposed expansion case to a structured case review or enroll in the MARPE course to refine appliance design, imaging interpretation, and contingency planning. Key sources: Chun, 2022, BMC Oral Health, doi:10.1186/s12903–022-02138-w. Jeon, 2022, Clinical Oral Investigations, doi:10.1007/s00784–021-04281–0. Benetti, 2024, dentistry journal, doi:10.3390/dj12030060.

